

How to Fix Camel Toe: Clothing, Anatomy and Surgery
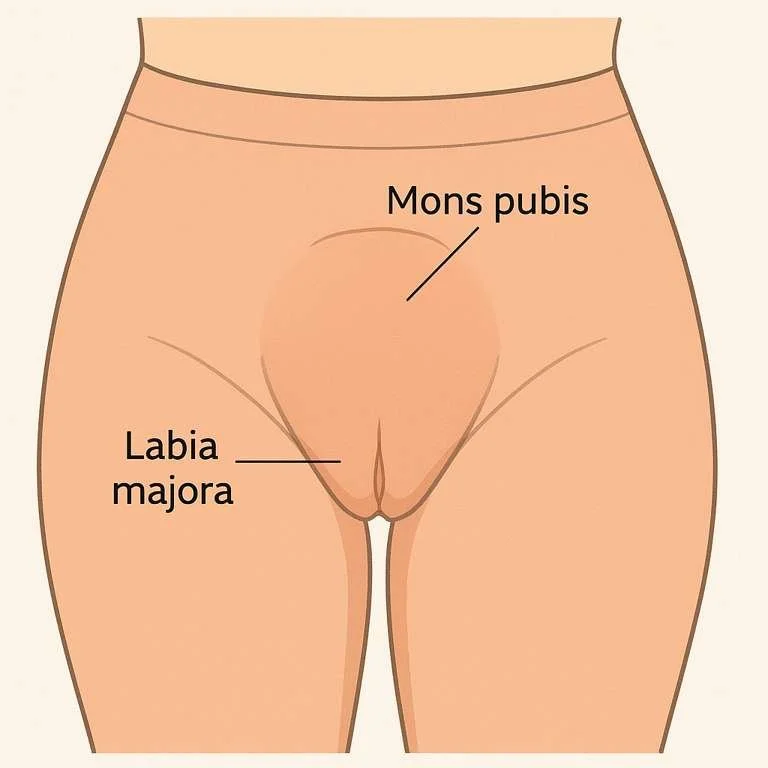
“Camel toe” is a slang term for a visible outline or central crease of the external vulva through clothing. Most often, it reflects the interaction between normal anatomy and clothing tension, not a medical condition. Tight or short-rise garments, a central front seam, thin stretch fabric, body position and the natural contours of the labia majora or mons can all make the outline more visible. If changing the garment changes the appearance, surgery is usually not the first answer. A surgical consultation becomes more relevant only when there is a persistent anatomical concern, such as symptomatic labia minora, excess outer-labial tissue or a prominent mons, that exists beyond one particular pair of leggings.
Key Takeaways
- Camel toe is an appearance through clothing, not a diagnosis and not evidence that something is wrong with the vagina.
- Start with the garment. Front-seam tension, rise, sizing, fabric stretch and underwear can make normal vulvar contours much more visible.
- Visible labia minora, fuller labia majora and mons fullness can all be normal anatomy. ACOG emphasizes that vulvar size, shape, color and symmetry vary widely.
- Labiaplasty treats labia minora. Labia majora reduction treats excess outer-labial tissue. Monsplasty or liposuction addresses the mons. These are different procedures and should not be used interchangeably.
- Surgery should solve a clearly identified anatomical concern, not simply a clothing problem that disappears when the fit or fabric changes.
What actually causes camel toe?
The visible outline usually appears when clothing places upward or inward tension across the vulva. The fabric then follows the natural contours underneath it. That can happen to someone with completely typical anatomy.
ACOG's vulvovaginal health guidance emphasizes that the vulva has a wide range of normal appearances. The labia majora vary in width, the labia minora may extend beyond the outer labia, and the two sides are often unequal. None of those features automatically requires correction.
| Possible contributor | What you may notice | Best first question |
|---|---|---|
| Clothing fit or front seam | Outline appears in some leggings, shorts or swimwear but not others | Does changing the garment, rise or seam remove the problem? |
| Natural labia majora contour | Outer-labial outline is visible through very fitted fabric | Is there actual discomfort or excess tissue outside clothing? |
| Labia minora projection | Inner tissue may bunch, twist or become visible in certain garments | Is the tissue causing persistent pulling, chafing or pinching? |
| Mons pubis fullness | Higher central pubic bulge rather than a lower labial crease | Is the concern actually the mons rather than the labia? |
| Outer-labial skin excess | Drooping or redundant labia majora tissue may create bulk | Is the problem excess skin, excess volume or both? |
| New swelling or skin change | Sudden asymmetry, pain, lump, redness or persistent swelling | Does this need medical evaluation rather than cosmetic treatment? |
1. Clothing can create camel toe even with normal anatomy
The most important correction to the current live article is that camel toe does not necessarily have a “root anatomical cause.” Sometimes the root cause is simply the garment.
A central front seam can pull upward. A rise that is too short for the torso can increase crotch tension. Thin stretch fabric can closely reproduce the contours underneath it. Sizing down can increase tension, while some underwear seams or fabric bunching can add another layer of pressure.
If the appearance changes substantially when you switch garments, that is useful information. It means changing the body surgically to fit one clothing design would be a disproportionate response.
2. Visible or uneven labia are usually normal
The internet often converts ordinary anatomy into labels such as “fat labia,” “too much skin” or “labial hypertrophy.” Those terms can make normal variation sound pathological.
ACOG states that there is no single correct vulvar appearance and that labia minora commonly extend beyond the labia majora. Its clinical guidance also warns against marketing normal genital variation as a condition requiring surgery. ACOG's guidance on elective female genital cosmetic surgery recommends evaluating the individual's actual symptoms and concerns rather than using size measurements as a threshold for surgery.
The Adonis labial hypertrophy guide is the better place to evaluate persistent pulling, chafing or symptomatic labial prominence. Camel toe by itself does not establish hypertrophy.
3. Labia minora and labia majora are not the same problem
The current article groups prominent inner and outer labial tissue together, but the surgical implications are different.
Labiaplasty most commonly reduces or reshapes the labia minora. ASPS describes its principal functional role as reducing tissue that twists, tugs or causes irritation. ASPS labiaplasty guidance does not present the operation as a generic treatment for every visible vulvar contour.
Labia majora reduction addresses the outer, hair-bearing labia when there is actual excess skin or bulk. ASPS describes labia majoraplasty as a separate operation designed to reduce the size of the outer labia. ASPS labia majoraplasty guidance also notes an important opposite problem: when the outer labia are deflated rather than excessive, volume restoration rather than reduction may be appropriate.
That is why “make the labia smaller” is not a diagnosis.
4. Mons fullness can be mistaken for a labial problem
The mons pubis is the soft tissue over the pubic bone, above the labia. A prominent mons can create a central bulge in fitted pants even when the labia themselves are not the main issue.
ASPS describes monsplasty as reduction of excess mons skin and/or fatty tissue, with liposuction being sufficient in selected cases. This is anatomically different from labiaplasty.
Adonis does not currently publish a dedicated monsplasty service page, so this article should not imply that mons surgery is a standard Adonis offering. If the concern appears to originate from the mons, the consultation should first establish the anatomy and whether an appropriate treatment is available.
What should you try before considering surgery?
If the concern is primarily how the area looks in clothing, start with reversible changes:
- compare the same outfit in the correct size and one size larger
- try garments without a central front seam
- compare different rises to reduce upward crotch tension
- choose a thicker or more structured fabric
- try smooth, well-fitting underwear that does not bunch
- compare how the outline changes when standing, walking and sitting
These are not medical treatments. They are a simple diagnostic step. If one pair of leggings creates the outline and another does not, you have learned that garment construction is a major contributor.
Useful self-check: before asking “Which surgery fixes camel toe?” ask “What exactly is creating the outline: the garment, inner labial tissue, outer labial tissue, the mons, or a combination?”
When can labiaplasty make sense?
Labiaplasty may be reasonable when labia minora are independently causing a problem, such as repeated twisting, pinching, chafing, pulling during exercise or intercourse, or a persistent aesthetic concern that remains meaningful after understanding normal variation.
The current Adonis labiaplasty service page takes the correct approach: the surgeon identifies which tissue is causing the concern and may recommend surgery, waiting, or no treatment at all.
Labiaplasty should not be promised to eliminate every clothing outline because the labia minora are only one possible contributor. Changing them cannot redesign a tight front seam, reduce mons fullness or address excess labia majora tissue.
When can labia majora reduction make sense?
Labia majora reduction is a different discussion. It can be relevant when the outer labia themselves have excess skin, bulk or drooping that remains apparent outside one specific item of clothing.
The Adonis labia majora reduction guide explains this distinction in more detail. Importantly, volume excess and volume loss require opposite strategies. Someone with deflated outer labia should not be treated as though the problem is simply “too much labia.”
What about “labia puffing correction”?
The current live article lists “labia puffing correction” as though it were a standard reduction procedure. That wording is confusing and should be removed.
Labia majora augmentation is generally intended to add volume when the outer labia have lost fullness. Reduction removes excess tissue. Those are opposite goals. A patient who previously had augmentation and now has too much volume needs individualized assessment of what material or tissue is present rather than a generic “puffing correction.”
Hair removal does not fix the anatomical cause
The current article also suggests grooming may reduce volume or friction. Pubic hair can influence how clothing feels, but removing hair does not reduce the labia or mons. ACOG notes there is no medical or hygiene requirement to remove pubic hair and that shaving or waxing can itself cause irritation or injury.
Hair removal therefore should not be presented as a treatment for camel toe anatomy.
When should you see a gynecologic clinician instead of treating this as cosmetic?
A long-standing outline in fitted clothing is very different from a new lump, painful swelling or skin change.
Seek medical evaluation if you notice:
- a new or rapidly enlarging lump
- new one-sided swelling
- persistent pain, burning or itching
- skin color or texture changes that do not resolve
- drainage, sores or recurrent inflammation
- symptoms that occur regardless of clothing
ACOG specifically recommends evaluation for persistent vulvar skin changes, new bumps, painful swelling, itching or burning. Surgery for appearance should not substitute for diagnosis of a medical problem.
How should you decide whether any permanent procedure is worth it?
A permanent procedure makes the most sense when three things are true: the concern is anatomically identified, it persists outside a particular garment, and the expected surgical change actually matches that anatomy.
The Adonis female genital cosmetic surgery options guide compares the relevant structures and procedures. The important safeguard is to avoid choosing an operation from a slang term. “Camel toe” describes what clothing shows; it does not tell the surgeon what tissue, if any, should be changed.
Honest limitation: there is little clinical research on “camel toe” itself because it is not a medical diagnosis. Evidence comes from established knowledge about normal vulvar variation and from the specific procedures used for symptomatic labia minora, excess labia majora tissue or mons prominence. No operation can guarantee that every pair of leggings, swimsuit or fitted pants will create a perfectly smooth contour afterward.
Frequently Asked Questions
What causes camel toe?
Usually it is the interaction between normal external anatomy and clothing tension. Tight garments, a short rise, a central front seam and thin stretch fabric can outline the labia majora or mons. Labia minora projection, fuller outer labia or mons fullness can contribute, but none of those features is automatically abnormal.
Does camel toe mean my labia are too big?
No. ACOG emphasizes that vulvar size, shape and symmetry vary widely and that labia minora often extend beyond the labia majora. If the outline appears only in certain clothing, garment fit may be the main cause. Labial size becomes a surgical question only when there is a separate persistent concern or symptom.
How can I fix camel toe without surgery?
Start by changing the garment variables: try a different size, a longer rise, no central front seam, a thicker fabric or smoother underwear. These changes do not alter your anatomy, but they often reduce how closely fabric follows the vulvar contour. If they work, surgery is usually unnecessary for the clothing issue itself.
Can labiaplasty get rid of camel toe?
Only in selected cases where projecting labia minora are a meaningful contributor. Labiaplasty does not change a tight front seam, mons fullness or excess labia majora tissue. The surgeon should identify the actual structure creating the concern before suggesting any operation, and no procedure should guarantee a perfectly smooth appearance in every garment.
Is labia majora reduction the same as labiaplasty?
No. Labiaplasty usually refers to reduction or reshaping of the labia minora. Labia majora reduction treats excess skin or bulk in the outer, hair-bearing labia. The two areas have different anatomy and different surgical trade-offs, so the procedure should match the actual source of the concern.
Can mons liposuction fix a camel toe appearance?
It may reduce a higher pubic bulge when localized mons fat is actually the problem, but it will not change prominent labia minora or excess labia majora skin. Some patients need skin removal rather than liposuction, and others need no procedure. The first step is distinguishing the mons from the labia.
Identify the anatomy before choosing a permanent fix
If changing the garment solves the problem, there may be nothing to treat surgically. If a persistent labial or mons concern remains, the surgical team at Adonis Plastic Surgery can evaluate which structure is involved, explain normal variation and discuss whether a procedure is appropriate or unnecessary.
Request a ConsultationReferences
Adonis Plastic Surgery is located at 2557 Pacific Coast Highway in Torrance, California, serving patients across the South Bay including Redondo Beach, Palos Verdes, Manhattan Beach, El Segundo, San Pedro, Long Beach, Carson and Gardena.
